
EFM Category 1: Complete Training Guide to Electronic Fetal Monitoring Requirements
Master efm cat 1 with our complete training guide. Learn requirements, documentation, and pass your C-EFM exam. ✅ Free practice questions included.

If you are preparing for the C-EFM certification or working to deepen your clinical knowledge in obstetric nursing, understanding efm category 1 is your essential starting point. EFM Cat 1 refers to the baseline fetal heart rate tracing category defined by the National Institute of Child Health and Human Development (NICHD) as a normal, reassuring pattern that requires no immediate intervention. Recognizing this category accurately is not simply a test-taking skill — it is a core competency that directly influences patient safety in labor and delivery units across the United States. Practice with the free EFM - Electronic Fetal Monitoring practice test on PracticeTestGeeks (11 questions with answer explanations).
Category I fetal heart rate tracings are characterized by a baseline rate between 110 and 160 beats per minute, moderate variability (amplitude of 6 to 25 beats per minute), the absence of late or variable decelerations, and the presence or absence of early decelerations and accelerations. When all of these features are present simultaneously, the tracing is considered Category I, indicating that the fetus is well-oxygenated and acid-base status is normal at that moment in time. This is a dynamic assessment, meaning a tracing that starts as Category I can evolve into Category II or III as labor progresses.
For nurses, midwives, and obstetric providers sitting for AWHONN or NCC examinations, EFM Category 1 knowledge forms the foundation of the entire electronic fetal monitoring framework. The NICHD classification system — which includes Category I, II, and III — was designed to standardize communication among care providers and eliminate the ambiguity that historically led to inconsistent clinical responses. Without a thorough grasp of what constitutes a normal (Category I) tracing, it is impossible to correctly identify and respond to abnormal (Category II or III) patterns.
This guide covers everything you need to know about EFM Category 1, from the precise physiological definitions to the documentation standards required in clinical practice. We will walk through the components of the normal fetal heart rate tracing, explain why each feature matters from a physiological standpoint, and provide concrete study strategies for mastering this content before exam day. Whether you are a new graduate nurse entering labor and delivery or an experienced clinician refreshing your knowledge for recertification, this guide is structured to help you succeed.
Electronic fetal monitoring has been a standard of care in U.S. labor and delivery units since the 1970s, and the ability to interpret tracings correctly remains one of the most critical and frequently tested competencies in perinatal nursing. Research consistently shows that poor communication about fetal heart rate patterns — including failure to recognize and document Category I tracings accurately — contributes to adverse neonatal outcomes and medical-legal liability. Understanding the boundaries of Category I and the clinical actions (or non-actions) it requires is foundational knowledge.
Throughout this article, you will find structured study tools, practice quiz links, and evidence-based explanations designed to build both your test-taking confidence and your clinical competency. The content aligns with the AWHONN Fetal Heart Monitoring Principles and Practices curriculum, the NCC C-EFM examination blueprint, and current ACOG guidelines. Use this guide alongside our free practice tests to reinforce your learning and identify any knowledge gaps before your exam date.
Free EFM - Electronic Fetal Monitoring Study Tools
Interactive EFM - Electronic Fetal Monitoring resources on PracticeTestGeeks, free to start:
- Free EFM Clinical Interpretation Questions and Answers — 11 questions with instant scoring and answer explanations
- EFM - Electronic Fetal Monitoring flashcards — review key terms and concepts card by card
- EFM - Electronic Fetal Monitoring study guide — topic-by-topic overview of what the exam covers
- EFM - Electronic Fetal Monitoring cheat sheet — one-page printable summary for last-minute review
- The NCC Electronic Fetal Monitoring exam has 125 questions; 100 are scored and the rest are unscored pretest items. (National Certification Corporation)
- Candidates get two hours to complete the NCC C-EFM exam. (National Certification Corporation)
- The C-EFM exam has no fixed passing percentage; NCC scores it pass/fail against a predetermined ability standard, using equating across exam forms. (National Certification Corporation)
- The NCC Electronic Fetal Monitoring (C-EFM) computer exam costs $210: a $50 non-refundable application fee plus a $160 testing fee. (National Certification Corporation)
- C-EFM retest candidates must wait 45 days after their exam before reapplying, and the exam can be taken only twice in a calendar year. (National Certification Corporation)
- NCC C-EFM certification is awarded for three years. (National Certification Corporation)
- The C-EFM exam is taken by computer, either at a test center or online through Live Remote Proctoring. (National Certification Corporation)
- To sit for the C-EFM exam, candidates need a current, unencumbered US or Canadian license as a physician, registered nurse, nurse practitioner, nurse midwife or midwife, physician assistant, or paramedic. (National Certification Corporation)
Facts verified Oct 19, 2026 against National Certification Corporation. Dates that have passed are removed automatically.
EFM Exam at a Glance
| Item | Detail | Official source |
|---|---|---|
| Number of questions | 125 questions (100 scored, 25 pretest) | National Certification Corporation |
| Time limit | 2 hours | National Certification Corporation |
| Passing score | Pass/fail against a predetermined ability standard (no set percentage) | National Certification Corporation |
| Exam fee | $210 (includes $50 non-refundable application fee) | National Certification Corporation |
| Retake policy | Wait 45 days; at most twice per calendar year | National Certification Corporation |
| Validity | 3 years | National Certification Corporation |
| Delivery | Computer test center or Live Remote Proctoring (PSI) | National Certification Corporation |
| Eligibility | Active US/Canadian license as physician, RN, NP, nurse midwife/midwife, PA or paramedic | National Certification Corporation |
| Testing window | Rolling 90-day eligibility window; schedule within the first 30 days | National Certification Corporation |
Facts verified Oct 19, 2026 against National Certification Corporation. Dates that have passed are removed automatically.
EFM Category 1 by the Numbers

C-EFM Exam Format Overview
| Section | Questions | Time | Weight | Notes |
|---|---|---|---|---|
| Fetal Heart Rate Interpretation | 51 | ~54 min | 30% | Includes Category I, II, III classification |
| Physiology & Pathophysiology | 34 | ~36 min | 20% | Oxygen pathway, uteroplacental function |
| Patient Safety & Quality Improvement | 29 | ~30 min | 17% | Communication, teamwork, documentation |
| Instrumentation & Technology | 22 | ~23 min | 13% | Equipment, artifact recognition |
| Clinical Management | 34 | ~37 min | 20% | Interventions, escalation, documentation |
| Total | 170 | 3 hours | 100% |
The NICHD classification system defines a Category I fetal heart rate tracing by five specific features that must all be present simultaneously. First, the baseline fetal heart rate must fall between 110 and 160 beats per minute. A rate below 110 bpm is classified as bradycardia, while a rate above 160 bpm constitutes tachycardia — either of which immediately moves the tracing out of Category I. The baseline is determined over a minimum 10-minute window, excluding periods of marked variability, accelerations, or decelerations.
Second, the tracing must demonstrate moderate baseline variability, defined as amplitude fluctuations of 6 to 25 beats per minute. Variability reflects the interplay between the sympathetic and parasympathetic nervous systems and is considered the single most important indicator of fetal central nervous system integrity. Absent variability (undetectable amplitude), minimal variability (1 to 5 bpm), or marked variability (greater than 25 bpm) all result in a Category II classification. Only moderate variability qualifies as Category I and signals a healthy, well-oxygenated fetal autonomic nervous system.
Third, accelerations may be present or absent in a Category I tracing — their presence is reassuring but their absence alone does not disqualify a tracing from Category I status. An acceleration is defined as a visually apparent, abrupt increase in FHR above baseline, with onset to peak in less than 30 seconds. At 32 weeks gestation or beyond, an acceleration must reach a peak at least 15 bpm above baseline and last at least 15 seconds but less than 2 minutes. Before 32 weeks, the threshold is 10 bpm above baseline lasting at least 10 seconds.
Fourth, late decelerations and variable decelerations must be absent for a tracing to be classified as Category I. Late decelerations are gradual decreases in FHR that begin after the peak of a uterine contraction and return to baseline after the contraction ends. They reflect uteroplacental insufficiency and, when recurrent, indicate that the fetus may not be receiving adequate oxygen. Variable decelerations are abrupt decreases in FHR that vary in timing relative to uterine contractions and are associated with umbilical cord compression. Either pattern disqualifies a tracing from Category I.
Fifth, early decelerations may be present or absent in a Category I tracing. Early decelerations are gradual, symmetric decreases in FHR that mirror uterine contractions — beginning with the onset of the contraction and returning to baseline as the contraction ends. They are caused by fetal head compression during labor, which triggers a vagal response, and are considered a benign, normal finding. Their presence neither confirms nor excludes Category I status, but their absence is equally acceptable. Understanding this nuance is frequently tested on the C-EFM examination.
Clinically, the appropriate response to a Category I tracing is continued monitoring with routine documentation according to your institution's policy. No immediate intervention is required. However, it is critical to understand that Category I status is a snapshot in time, not a permanent designation. A tracing that is Category I at 8:00 AM may evolve into a Category II or III pattern by 9:00 AM as labor intensifies, maternal position changes, or uterine hyperstimulation develops. Continuous reassessment is therefore essential even when the current tracing appears completely normal.
Documentation of a Category I tracing in the medical record should include the specific features observed: baseline rate, variability description, presence or absence of accelerations, and absence of significant decelerations. Many institutions use standardized language aligned with NICHD terminology to ensure clear communication among all members of the care team. Using vague or non-standardized terms such as "looks good" or "reassuring strip" without specific feature documentation is considered inadequate and increases medicolegal risk. Always document the full NICHD classification along with the clinical rationale for any management decision.
EFM Category 1 Clinical, Legal, and Training Standards
The clinical standard for Category I EFM management is systematic, ongoing assessment documented at regular intervals per institutional policy. AWHONN recommends that low-risk patients in active labor have their FHR tracing assessed and documented at least every 30 minutes during active labor and every 15 minutes during the second stage. For high-risk patients, assessment frequency increases to every 15 minutes in active labor and every 5 minutes during pushing. Even with a Category I tracing, nurses must remain vigilant for tracing evolution and respond promptly to any changes in pattern.
Clinicians should also be alert to subtle shifts within Category I that may signal emerging fetal stress before the tracing formally crosses into Category II territory. For example, a gradual reduction in variability from the moderate range toward the minimal range, or the emergence of periodic decelerations that have not yet become recurrent, warrants increased surveillance and potentially earlier escalation to the provider. Clinical judgment informed by the full clinical picture — including maternal vital signs, contraction frequency, and labor progress — must always accompany EFM interpretation.

Continuous EFM vs. Intermittent Auscultation: Key Tradeoffs
- +Continuous EFM provides a permanent, reviewable record of fetal heart rate throughout labor
- +Category I identification is straightforward and consistent with electronic tracings
- +Electronic FHR monitoring allows simultaneous assessment of contraction frequency and duration
- +Category changes from I to II or III are immediately visible on the continuous strip
- +Required by ACOG for high-risk pregnancies and widely used for all laboring patients
- +Supports team communication by providing a shared visual reference for all providers
- −Continuous EFM restricts maternal mobility and may increase patient discomfort
- −Higher false-positive rate for Category II classification can lead to unnecessary interventions
- −Technical artifacts and signal loss can mimic or obscure genuine FHR pattern changes
- −Requires ongoing staff training and competency validation to interpret correctly
- −Overreliance on the monitor may reduce direct patient assessment and nurse-patient interaction
- −Interobserver variability in Category I vs. II classification remains a documented limitation
Pros and Cons at a Glance
| Pros | Cons |
|---|---|
| Continuous EFM provides a permanent, reviewable record of fetal heart rate throughout labor | Continuous EFM restricts maternal mobility and may increase patient discomfort |
| Category I identification is straightforward and consistent with electronic tracings | Higher false-positive rate for Category II classification can lead to unnecessary interventions |
| Electronic FHR monitoring allows simultaneous assessment of contraction frequency and duration | Technical artifacts and signal loss can mimic or obscure genuine FHR pattern changes |
| Category changes from I to II or III are immediately visible on the continuous strip | Requires ongoing staff training and competency validation to interpret correctly |
| Required by ACOG for high-risk pregnancies and widely used for all laboring patients | Overreliance on the monitor may reduce direct patient assessment and nurse-patient interaction |
| Supports team communication by providing a shared visual reference for all providers | Interobserver variability in Category I vs. II classification remains a documented limitation |
EFM Category 1 Study Checklist: 10 Must-Know Competencies
- ✓Memorize the five defining features of a Category I tracing per NICHD 2008 guidelines
- ✓Practice calculating and describing FHR baseline from a 10-minute strip segment
- ✓Distinguish all four variability categories: absent, minimal, moderate, and marked
- ✓Identify the difference between accelerations before and after 32 weeks gestation
- ✓Recognize early decelerations and confirm they do not exclude Category I classification
- ✓Confirm absence of late and variable decelerations for a valid Category I designation
- ✓Practice using SBAR format to communicate about a Category I to Category II tracing transition
- ✓Review your institution's documentation policy and required charting intervals for Category I
- ✓Complete at least 3 full-length EFM practice quizzes focusing on Category I identification
- ✓Study the physiological basis of moderate variability and why it reflects CNS integrity

Moderate Variability Is the Single Most Reassuring EFM Feature
Of all the components required for a Category I designation, moderate variability (6–25 bpm amplitude) carries the greatest clinical weight. Research and the NICHD consensus panel both affirm that moderate variability is the strongest predictor of a non-acidotic fetal status. When variability is present and moderate, it provides significant reassurance even when other features are ambiguous. Conversely, absent variability combined with late or variable decelerations is the hallmark of a Category III tracing requiring immediate intervention.
One of the most common sources of confusion for nurses and exam candidates alike is understanding how to differentiate Category I from Category II tracings when the findings are subtle or borderline.
The NICHD classification was deliberately designed with Category II as a broad, heterogeneous category that captures all tracings that are neither clearly normal (Category I) nor clearly abnormal (Category III). This means that any tracing with even a single feature outside the Category I criteria — such as a baseline that drifts to 108 bpm or variability that appears consistently in the 4 to 5 bpm range — must be classified as Category II, even if all other features are reassuring.
Understanding the physiological mechanisms behind each feature of the fetal heart rate tracing helps clinicians and exam candidates avoid rote memorization errors. The FHR baseline is regulated primarily by the autonomic nervous system, with the parasympathetic system (mediated by the vagus nerve) and sympathetic system maintaining a dynamic balance that produces the characteristic variability seen in healthy fetuses. When a fetus becomes hypoxic or acidotic, the central nervous system's ability to modulate autonomic outflow is compromised, leading first to loss of variability and eventually to the reflex decelerations associated with Category II and III patterns.
Accelerations are another key teaching point. They reflect a functionally intact fetal nervous system capable of mounting a sympathetic response to fetal movement or uterine contractions. The presence of spontaneous accelerations — sometimes called reactive accelerations — is the basis for a reactive nonstress test (NST), which is considered evidence of fetal well-being in the antepartum period. During labor, accelerations are not required for Category I classification, but their presence provides additional reassurance. Their sudden disappearance during labor, particularly when combined with a decrease in variability, should prompt closer surveillance and possible provider notification.
Early decelerations are frequently misidentified on examinations because they share superficial similarities with late decelerations in their gradual, smooth waveform shape. The critical distinguishing feature is timing: early decelerations mirror the contraction, with the nadir occurring at the peak of the contraction and recovery coinciding with the end of the contraction. Late decelerations, by contrast, begin after the contraction peaks and fail to return to baseline until after the contraction has ended. This 20 to 30 second time lag is the hallmark of late deceleration and reflects delayed oxygen delivery through the intervillous space during placental compression.
Variable decelerations represent a distinct mechanism — umbilical cord compression — and are characterized by their abrupt onset and variable morphology. The term "variable" refers to the variability in shape, depth, and duration from one deceleration to the next, not variability in the baseline. On the C-EFM examination, questions about variable decelerations often test the candidate's ability to identify associated features such as shoulders (small accelerations before and after the deceleration), the presence of a W shape, or loss of the characteristic V morphology, all of which carry prognostic significance in Category II assessments.
When transitioning from Category I to Category II during labor, the clinical response should follow a systematic approach. First, perform a thorough bedside assessment to identify any correctable cause of the tracing change, such as maternal hypotension, uterine hyperstimulation, maternal fever, or cord prolapse. Interventions such as lateral repositioning, IV fluid bolus, oxygen administration, and reduction or cessation of oxytocin are often the first-line responses. Notify the provider using structured communication tools such as SBAR or CUS (Concerned, Uncomfortable, Safety concern) to ensure that the urgency of the situation is clearly conveyed.
From an exam preparation standpoint, many C-EFM candidates find it helpful to study Category I in direct contrast with Category II and III, rather than in isolation. By learning the spectrum of each feature from normal to abnormal — for example, practicing identifying baseline rates from 90 to 170 bpm across a series of strip images — candidates build the pattern recognition skills needed to classify tracings quickly and accurately under timed exam conditions.
Our free practice quizzes are designed with this comparative learning approach in mind, presenting tracings across all three categories and asking you to identify the specific feature or combination of features that determines the classification.
If you want more targeted practice, the efm tracing game page covers the same material with additional questions and explanations.
A Category I tracing reflects the fetal status at that specific moment in time and should never be interpreted as a guarantee that the fetus will remain well-oxygenated throughout labor. Tracings can transition from Category I to Category II or III within minutes due to acute events such as placental abruption, cord prolapse, or uterine rupture. Continuous assessment, timely documentation, and proactive communication with the obstetric provider remain essential even when the current tracing is fully reassuring.
Effective preparation for the EFM Category 1 content on the C-EFM examination requires a combination of conceptual understanding, strip interpretation practice, and familiarity with the standardized language used in both clinical documentation and exam questions. Many candidates make the mistake of focusing exclusively on memorizing definitions without developing the perceptual skills needed to visually identify the features of a Category I tracing on an actual strip. The C-EFM exam presents tracing images in multiple formats, and candidates must be able to classify them quickly and accurately under timed conditions.
One highly effective study strategy is to use a systematic four-step interpretation method for every strip you practice with. Step one: determine the baseline by identifying the predominant rate over a 10-minute window, rounding to the nearest 5 bpm. Step two: assess variability by measuring the amplitude of the highest and lowest peaks within a one-minute window, excluding accelerations and decelerations. Step three: identify any accelerations, noting their onset, peak height above baseline, and duration. Step four: identify any decelerations, determining their type (early, late, variable, or prolonged) based on timing relative to uterine contractions and onset characteristics.
This systematic approach prevents the common error of categorizing a tracing based on a quick gestalt impression rather than a methodical evaluation of each feature. On the C-EFM exam, distractors are carefully designed to exploit exactly this kind of shortcut thinking. For example, a tracing with a normal baseline and apparent moderate variability may contain recurrent late decelerations that are shallow and easily overlooked — but their presence immediately moves the tracing to Category II regardless of how reassuring the other features appear.
Another important study area for EFM Category 1 is the intersection between EFM interpretation and clinical communication. The C-EFM examination places significant weight on communication and teamwork competencies, reflecting the evidence that communication failures are a leading contributing factor in adverse perinatal outcomes. Candidates should be familiar with the SBAR framework (Situation, Background, Assessment, Recommendation) and the CUS tool, as well as the concept of closed-loop communication in which the receiver confirms the message received back to the sender.
Documentation questions on the C-EFM exam often present scenarios in which a nurse must decide what to chart, when to chart, and how to communicate findings to the provider. Understanding that Category I requires routine documentation at policy-defined intervals — and that any change in category requires immediate documentation and provider notification — helps candidates answer these scenario-based questions correctly. Institutional policies vary, but the underlying principles of timely, specific, and standardized documentation are consistent across all AWHONN and NCC guidance.
For candidates who have already completed AWHONN's Fetal Heart Monitoring Principles and Practices course, the C-EFM exam content will feel familiar in structure and terminology. However, the exam goes beyond course content by presenting complex clinical scenarios that require candidates to synthesize knowledge from multiple domains simultaneously. Practicing with exam-style questions — particularly those that combine EFM interpretation with clinical management decisions — is the most effective way to prepare for this level of complexity. Resources like our C-EFM Certification guide provide additional strategies for exam day success.
Group study sessions with colleagues from your labor and delivery unit can also be a powerful preparation strategy. Reviewing actual de-identified strips together, discussing classification disagreements, and practicing verbal communication using SBAR all reinforce both the knowledge and the clinical reasoning skills assessed by the C-EFM exam. Peer discussion also helps surface knowledge gaps that solo studying may miss, particularly in areas where individual nurses have developed habits or assumptions that differ from the standardized NICHD definitions.
As you move into the final weeks of your C-EFM exam preparation, it is important to shift your focus from knowledge acquisition to active recall and timed practice. Research on effective learning consistently shows that retrieval practice — actively pulling information from memory rather than passively rereading notes — produces significantly stronger long-term retention than any form of passive study. Use our free EFM practice tests in timed mode to simulate actual exam conditions, and review every incorrect answer in detail to understand the reasoning behind the correct choice.
Pay particular attention to questions that require you to distinguish between Category I and Category II tracings based on a single ambiguous feature. These questions are intentionally designed to test the precision of your knowledge. For example, a question might present a tracing with a baseline of 162 bpm and moderate variability with no decelerations, asking for the NICHD classification.
The correct answer is Category II — not Category I — because the baseline exceeds 160 bpm, the upper boundary of Category I. Without a precise command of each feature's numerical boundaries, it is easy to select the intuitively appealing but incorrect answer of Category I.
Time management on the C-EFM exam is another critical preparation focus. With 170 questions to complete in 3 hours, candidates have approximately 63 seconds per question. EFM strip interpretation questions — which require visual analysis before reading the answer choices — tend to be the most time-consuming. Practice completing strip-based questions in under 90 seconds by drilling your systematic four-step interpretation method until it becomes automatic. For text-based scenario questions, use the process of elimination aggressively: identify and eliminate clearly incorrect answers first, then choose between the remaining options based on the most specific and clinically accurate reasoning.
Nutrition, sleep, and mental preparation matter more than most candidates expect in the final days before the exam. The C-EFM is a challenging, high-stakes assessment, and cognitive fatigue significantly impairs the pattern recognition skills central to EFM interpretation. Aim for at least 7 to 8 hours of sleep in the three nights before the exam, avoid cramming new content the night before, and arrive at the testing center with a full meal and sufficient time to complete check-in without rushing. Your goal on exam day is to perform at your best, not to learn new material.
After passing the C-EFM exam, your EFM knowledge base continues to develop through clinical experience, institutional competency programs, and ongoing education. AWHONN recommends that nurses in labor and delivery settings complete EFM competency validation annually, using a combination of written assessment and practical strip interpretation. Many hospitals also conduct regular case reviews of adverse outcome cases or near-misses in which EFM interpretation or communication played a role, providing valuable learning opportunities in a non-punitive environment.
The C-EFM credential is valid for three years, after which recertification is required either by retaking the examination or by completing 30 hours of approved continuing education in EFM topics. Staying current with updates to NICHD definitions, ACOG practice bulletins, and AWHONN guidance ensures that your clinical practice and exam knowledge remain aligned with evolving evidence. The field of EFM continues to generate new research, including studies on the predictive value of specific Category II patterns and the role of adjunct technologies such as fetal pulse oximetry and ST waveform analysis.
We encourage every candidate preparing for the C-EFM to use a full spectrum of study resources, combining structured curriculum, textbook review, strip interpretation practice, and exam-style question banks. Our platform offers free EFM practice quizzes aligned with the C-EFM exam blueprint, allowing you to assess your readiness by domain and identify specific areas that need additional attention before your test date. Consistent, deliberate practice across all content areas — with particular emphasis on EFM Category 1 as the foundation — is the proven path to passing this important certification examination.
Sample EFM - Electronic Fetal Monitoring Practice Questions
Try these questions from our free EFM - Electronic Fetal Monitoring practice tests. The correct answer and an explanation follow each question.
Which of the following is not considered a Category 3 fetal tracing?
- A. A sinusoidal pattern
- B. Recurrent late decelerations with minimal variability
- C. A prolonged deceleration with absent variability
- D. Recurrent variable decelerations with absent variability
Answer: B. Recurrent late decelerations with minimal variability
Explanation: Absent fetal heart rate variability is required for Category 3 tracings. Late decelerations with minimal variability is still Category 2.
A clinician has classified a fetal heart rate tracing as Category II. Which of the following findings, on its own, would be consistent with this classification?
- A. Moderate variability with no decelerations
- B. Sinusoidal pattern
- C. Marked variability
- D. Absent variability with recurrent variable decelerations
Answer: C. Marked variability
Marked variability (amplitude range >25 bpm) is an example of a finding that places a tracing into Category II. Moderate variability with no decelerations is a feature of Category I. A sinusoidal pattern or absent variability with recurrent variable decelerations would classify the tracing as Category III.
A nurse is concerned about a persistent Category II tracing with recurrent late decelerations. The attending physician was notified 30 minutes ago but has not come to the bedside or provided new orders. From a professional and legal standpoint, what is the nurse's most critical next action?
- A. Document the current time and wait another 15 minutes for the physician to respond.
- B. Ask a colleague for a second opinion on the fetal heart rate tracing.
- C. Initiate the established institutional chain of command.
- D. Administer a 500 mL IV fluid bolus and place the patient on her left side.
Answer: C. Initiate the established institutional chain of command.
The nurse has a professional and legal duty to advocate for patient safety. When the primary provider is unresponsive or there is a disagreement on the plan of care for a concerning clinical situation, the nurse must activate the hospital's chain of command to escalate the concern to the next level of authority (e.g., charge nurse, unit manager, chief of obstetrics). This ensures the situation is addressed promptly and fulfills the nurse's advocacy role. While the other actions are relevant, they do not resolve the critical issue of an unresponsive provider.
When documenting a category II fetal heart rate tracing, what is the MOST important element to record?
- A. Interventions performed and fetal response
- B. Only the strip interpretation label
- C. The nurse's personal opinion of fetal status
- D. The number of visitors in the room
Answer: A. Interventions performed and fetal response
Documenting the interventions performed and the fetal response demonstrates clinical action taken and establishes a clear record for continuity of care.
Take the full EFM - Electronic Fetal Monitoring practice test
EFM Questions and Answers

C-EFM Practice Questions: Free Electronic Fetal Monitoring Exam Prep (2026)
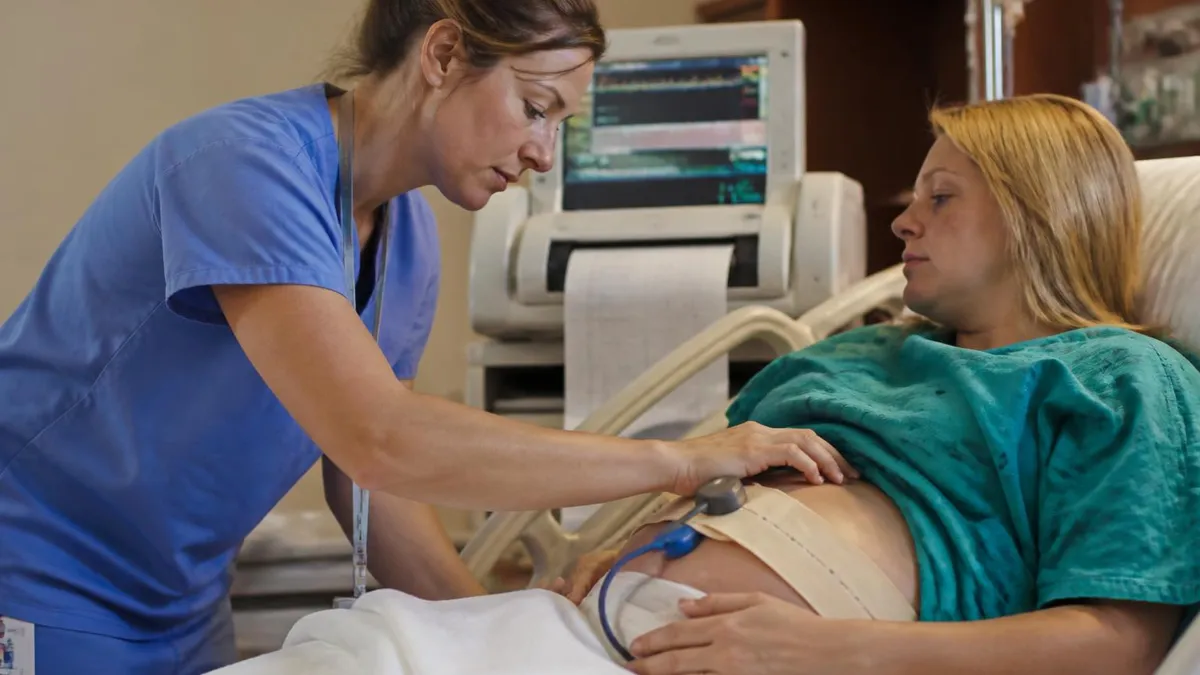
C-EFM Certification: Complete Study Guide and Exam Prep for 2026

EFM Guidelines: Complete Training Guide to Electronic Fetal Monitoring Requirements

EFM Books: The Complete Guide to Electronic Fetal Monitoring Study Resources

EFM Practice Test PDF (Free Printable 2026)
How this page was made: written with AI tools and published by Nathan Beja, founder of Practice Test Geeks, who is responsible for its content. Exam facts are checked against the official sources listed below. Not reviewed by a subject-matter expert. Editorial policy
Sources & references
Exam facts on this page (fees, format, dates, passing scores) are checked against these official sources; the date is our last check. Editorial policy
- nccwebsite.org — Fees, exam format, passing score, retake policy, score validity, eligibility, test delivery, time limit, exam information · verified Oct 2026